Double Board-Certified, Harvard-Trained

Skin Aging and Fractionated CO2 Laser Resurfacing

Over a lifetime the skin begins to wear out from the surface inward. Sun mottles the pigment of the epidermis; in the dermis beneath, collagen and elastin fibers begin to fragment and the skin loses resilience; on the outside one sees fine lines, atrophic scars, uneven color and a rougher texture. Topical products reach the surface layer and cannot rebuild the dermis, which is where resurfacing works.

A fractional carbon dioxide laser removes microscopic columns of skin (ablation), each rimmed by a thin zone of heat-coagulated collagen, and leaves the skin between them untouched. That untouched skin closes the wound within days, and the wound drives new collagen over the following three to six months.

Who is a candidate, and who is not

Fitzpatrick types I to III (skin that burns before it tans) are the well-documented candidates; the 2025 consensus panel named types I and II the ideal patient, and the published data come overwhelmingly from these types.

Type IV is treated conservatively, in staged mild-to-moderate sessions with pigment conditioning and counseling, or not with this technology at all: hyperpigmentation runs 55 to 68 percent in published type IV series, and only 12 percent of the panel treat type IV and above. Types V and VI are generally directed to non-ablative or energy-free alternatives; in a one-year series of types III to VI, 15 percent still had punctate hypochromia, all of them type V or VI, and that change is not reliably treatable.

Not candidates, or not yet, in the order in which each most often decides the question: patients who cannot stay out of the sun for four weeks and wear SPF 30 and a hat after that; who cannot take seven to ten days out of public view after a single deep session; whose main concern is loose or hanging skin; with an active herpetic lesion in the field, recent sunburn, or pregnancy or breastfeeding; who cannot safely receive intravenous sedation; or with a history of keloid or hypertrophic scarring, or current isotretinoin use, without a specific discussion first.

Patients are disappointed, even when the laser works, if they expect tightening, expect deep static folds to disappear (resurfacing softens the skin within a fold and does not remove it), expect one session to clear ice-pick scars, or judge the result at three weeks, while remodeling is still running. Resurfacing treats skin quality and not skin excess; a jowl or hanging neck skin calls for a facelift, mini face lift or neck lift.

What recovery actually looks like

Patients recover along one of two courses, each with its own written protocol: resurfacing alone, and resurfacing at the same sitting as a face or neck lift, which is not an average of the first.

Higher energy means a longer recovery, not a shorter one. A deeper, denser treatment is a larger wound, which closes more slowly and stays red longer, and sedation does not shorten what follows. One high-setting treatment averaged 7.3 days of downtime against 4.3 in total for staged lighter treatments; our sheet asks one to two weeks out of public view, and one should plan for the long side.

Laser resurfacing on its own

First 24 hours

Heat, redness, swelling and tenderness are expected; a responsible adult stays for 24 hours.

Days 1–3

Swelling peaks, with clear ooze, bronzing and a visible grid. Patients wash four to six times a day, with ointment after each wash, so crust does not form.

Days 3–10

The columns slough and peel. The skin closes by about day 7 at wrinkle depth and day 10 at scar depth, and near 13 days at deeper settings in darker skin.

Weeks 1–4

The one-week visit falls here, and patients avoid social exposure for one to two weeks. Redness fades over about four weeks, sometimes months; once initial healing has taken place, makeup can cover it. No sun for four weeks.

Week 4 onward

SPF 30 in the sun and the brimmed hat; a retinoid resumes at four to six weeks. Remodeling continues three to six months; delayed pigment loss, if it comes, comes months later.

Laser resurfacing at the same sitting as a face or neck lift

First 48 hours

The compression dressing stays until the first post-operative visit. Patients rest upright, on the back only, and the lasered skin is washed from 24 hours. Lift swelling peaks at 36 to 48 hours to day 3.

Days 2–7

Home dressing changes run six times a day, then five, then four, until the one-week visit. At least a week off work; incision crust and numbness are expected.

Weeks 2–3

Bruising lasts two to three weeks, longer in some; numbness continues, with tingling as sensation returns. Regular activity resumes at week 3.

Weeks 4–6

A retinoid restarts if Dr. Kim approves; SPF 30 begins, and the lasered skin leaves complete sun avoidance at four weeks. Oil-based makeup and heated tools return at week 5, hair color at week 6.

Months 2–12

Swelling and bruising may persist from a few weeks to a few months, and total recovery can take up to one year.

Two wounds, not one

In the one animal model that tested it, flaps lasered on the day of surgery healed in 23.9 days on average, slower than flaps lasered at day 7 or 14. The sheets give no combined figure, so one should plan on the longer course.

The risks, with published incidence

Figures from confluent, fully ablative treatment are labeled as such; fractional treatment has a very different profile.

Hyperpigmentation (darkening) is the dominant complication and depends on skin type: 95 percent of the 2025 panel have met it, and in type IV skin it ran 68 percent after fully ablative treatment and 55.5 percent at one month after a single fractional session (11.1 percent at six months). It is common, usually temporary, and not reliably prevented by any regimen. Hypopigmentation (lightening) is the late one: it may appear only six to twelve months after treatment, it is not reliably treatable, and it should be assumed permanent. Fractional delivery at moderate settings has largely reduced it, yet 47 percent of the panel have seen it, and depth and skin type, both decided beforehand, drive the risk.

Infection: 4.3 percent across 395 procedures, onset days two to ten, and more common with full-face treatment and with bio-occlusive dressings, which is why wound care here is open.

Herpes reactivation: 7.4 percent of 500 patients after fully ablative treatment; in a series that used antiviral prophylaxis, 90 percent of 99 patients had no recurrence, yet about one in three with a positive history still reactivated, so prophylaxis lowers the risk and does not remove it.

Redness and scarring: erythema averaged 4.5 months after fully ablative CO2 and ran under seven days across 108 moderate fractional sessions, with deep settings between; hypertrophic scarring was 0.46 percent across 1,093 patients, raised by depth, infection and picking.

Contact dermatitis: 67 percent of panelists have met it, mostly from what is put on the skin; itching with a spreading rash is more often a product reaction than an infection, and worth a call.

Eyelids and neck: no ectropion in 424 lower-eyelid treatments, with the risk at 6.25 percent when a transcutaneous lower blepharoplasty was combined with resurfacing. Neck skin has fewer adnexal structures to heal from, and 48 percent of the panel would not laser the neck of a laxity patient, so we treat it cautiously, at reduced settings, or not at the same time.

Intravenous sedation carries its own risks, reviewed individually before treatment. These figures describe study populations and not predictions for one patient; Dr. Kim reviews skin type, herpes history, medications, sun habits and healing history at consultation.

Why we treat under sedation, and what that does not prove

Resurfacing at treatment depth is performed in the practice's own AAAHC-accredited office-based surgical suite in Syracuse, a self-pay, cosmetic-only facility that does not use general anesthesia. Treatment is under local anesthesia with intravenous twilight sedation, given by our anesthesia provider and monitored throughout; the patient breathes unaided and most have no memory of it.

Pain rises with the same settings that drive the result, energy and density. Awake, full-face treatment at mild settings was rated 8.6 out of 10 with an emollient alone and 3.0 with the best topical cream, and 57 percent of a 21-member expert panel said topicals alone do not cover aggressive resurfacing. Awake, tolerance sets the ceiling on energy, density and passes.

Twilight sedation lifts that ceiling, and the surgeon's judgment and the patient's skin type become the limits. Higher energy and density give a deeper remodeling response from one session; the cost, set out in the recovery section, is a longer and more demanding recovery.

What this does not prove: no study has compared cosmetic results by anesthesia method, 91 percent of the panel said sedation is not required for full-face resurfacing, and excellent results are achieved awake every day. Sedation is not a safety feature, since it adds anesthetic risk; what makes it appropriate is the setting, with accreditation, monitoring and a provider whose only task is the patient.

The study that argues against our own positioning

A 2024 trial of 44 patients compared one treatment at high settings with two to three at low-to-moderate settings. The staged group scored better on most scales, reported higher satisfaction, had no adverse events and shorter downtime overall (4.3 days against 7.3), and both groups reached the same 51 to 75 percent band of global improvement.

On this evidence one deeper session buys fewer episodes (one anesthetic, one recovery) and not a better result, which matters to a patient traveling from Manhattan or Rochester and little to one who lives ten minutes away. Consensus follows skin type: a single high-setting treatment in types I and II, several mild-to-moderate treatments in types III and IV. A staged series is two to four sessions at six to eight week intervals.

Resurfacing at the same time as a facelift or eyelid surgery

A lift restores position and does not change the skin surface, so the two are commonly combined, with one real controversy: the flap. In a 2026 meta-analysis of 17 studies and 1,361 patients, laser at the time of facelift gave flap necrosis of 0.01 percent and skin slough of 0.21 percent, but lasering undermined skin at the same energy density as non-dissected skin was significantly associated with more slough.

The zone rule that follows: the non-undermined central face at full intended depth; the undermined lateral flap left alone or treated superficially at much lower settings; the neck cautiously or staged. Staged after a facelift, the consensus interval is six months, and at least three months after upper eyelid surgery. Which zones, at which sitting, depends on how much the operation undermines and is decided at consultation; a mini face lift and a deep-plane facelift are not the same situation.

The written protocol, in the order patients follow it

These are the instructions this practice gives in writing at the pre-operative visit (revised 2026). Practice protocol means our own rule, not settled fact.

Laser alone

From 24 hours the skin is washed gently with lukewarm or cool water four to six times a day, more if possible, with no soap; after each wash it is dabbed dry and a thick layer of Aquaphor goes on before the skin finishes air-drying, so that the skin never dries and crust never forms. Crust is never picked, and crust that will not wash off is left in place. The head sleeps raised on an extra pillow for two weeks. This is open care; infection was more common under bio-occlusive dressings, and four to six washes is practice protocol, not a tested number. At the one-week visit a Cetaphil or VaniCream cleanser may begin, unless Dr. Kim asks for longer on Aquaphor.

With a lift: the dressing routine

We remove the compression dressing at the first post-operative visit; the home routine then runs six times a day for two days, five for the next two, and four until the one-week visit, more often than any published facelift regimen we surveyed (practice protocol). Each change lifts the old Aquaphor away with clean Q-tips; where crust has formed along the suture line, a peroxide-soaked Q-tip is rolled over it only to dissolve the crust; then the skin is dried, generous Aquaphor goes over all incisions, flat stacks of folded gauze are placed, and the ace wrap goes on snugly with the ears flat and never folded. The lasered skin keeps the laser-only routine.

With a lift: where our protocol departs

The pillow goes between the neck and the shoulder, not behind the head, so the neck stays slightly extended and is never flexed with the chin toward the chest; the ear is never pulled forward; glasses sit on top of the compression wrap. Practice protocol: we recommend lymphatic drainage massage and give a tutorial; Dr. Kim's instructions describe it as reducing swelling through the face and neck, and patients speak to him before starting, since when to begin depends on how the flap is healing. No facelift-specific trial shows that manual lymphatic drainage changes the course of swelling, so the recommendation rests on clinical experience.

Throughout

Nicotine in any form is avoided absolutely. Aspirin and NSAIDs (ibuprofen, Motrin, Advil, Aleve) are avoided for bleeding risk, with acetaminophen the fallback. Fresh fruit and vegetables and water are asked for, and no alcohol or salty processed food (practice protocol). No driving for the first 24 hours, or the first week after a lift, and never on opioid medication.

When to call the office

Call 315-471-8404, or reach Dr. Kim outside office hours, for severe pain; a fever (the number is in the written instructions); increasing swelling or discoloration of the skin; thick honey-colored crusting or spreading redness; redness that suddenly worsens with intense itching (an Aquaphor reaction, answered with a prescription ointment); or tenderness with cold-sore-like blisters. After a lift, add excessive bleeding, discharge, flu-like symptoms and uncontrolled pain. We would also hear about any new pale or gray patch. Surgical patients have an on-call physician during off-hours and direct access to the surgeon; complications are easy to treat early and hard later, so one should call early, and go to the nearest emergency department if we cannot be reached.

Follow-up is two visits after laser alone, one at one week, and three with a lift, the first being where we remove the compression dressing. It is a good visit when the skin has closed and the patient sees it clearly for the first time, and it reminds us why we do this work.

What the laser does, and what sets the depth

The beam is carbon dioxide light at 10,600 nanometers, and its chromophore is tissue water, so it removes tissue and does not select a pigment. Energy per microbeam sets depth (mean ablation depth ran from 283 micrometers at 500 microseconds to 1.05 millimeters at 1,800), total energy and stacking set width and coagulation, and density sets how much of the surface is treated. Together they set how much collagen is made, how long recovery runs and how much risk is taken.

How we prepare the skin

Practice protocol: a prescription retinoid nightly from six weeks before treatment (a prescription combination cream in its place for darker complexions), stopped one week before the laser and resumed four to six weeks after. We condition the skin because it is reasonable and low-risk, not because it is proven; the consensus paper states that these regimens lack strong evidence for preventing hyperpigmentation. Other medications are reviewed individually at the pre-operative visit.

How long it lasts, and how the cost is built

The collagen made is the patient's own, and the result develops over three to six months. It is not permanent: photoaging continues because sun and time continue. SPF 30 in the sun, a brimmed hat and no smoking extend it, and scar improvement tends to hold.

We do not publish figures, because a number quoted before the skin is examined is a guess, and depth, area and anesthesia setting vary by a factor of several. The fee has three parts, the surgeon, the accredited suite and the anesthesia provider, and the full figure is given in writing first. Health insurance does not cover cosmetic resurfacing.

Other ways to treat the same problems

Fractional Er:YAG is comparable for wrinkles, hurts less and reddens about 1.85 days less, with a lower response in acne scars. Non-ablative fractional suits maintenance and patients who cannot take downtime, and is clearly weaker for scar. Microneedling and radiofrequency microneedling carry less downtime and pigment risk, particularly in darker skin, on mixed and mostly small trials; a deep chemical peel is effective perioral and shares the delayed-hypopigmentation concern.

Resurfacing is commonly combined with a facelift or mini face lift, a neck lift or neck liposculpt, facial fat transfer (volume, which no laser restores) and eyelid surgery. Results are in the gallery, and consultations are held at the Syracuse, Rochester and Manhattan offices, where skin type and calendar are assessed together. Schedule a consultation.

Laser Skin Resurfacing FAQs

Does CO2 laser resurfacing really work, and is it worth it?

It works, and the effect sizes are published: in a 45-patient series, investigators scored overall improvement at 52.4 percent, and acne-scar depth improved a mean 66.8 percent. It is worth it when skin quality is the problem. When the concern is loose or hanging skin it is the wrong procedure, and a good result will still disappoint.

Do I have to be awake for CO2 laser resurfacing?

No. Most practices treat awake, and excellent results are achieved that way. Awake, full-face treatment at mild settings was rated 8.6 out of 10 for pain with an emollient and 3.0 with the best topical cream, so tolerance limits how deep and dense treatment can go. Sedation moves that limit from tolerance to the surgeon's judgment.

Is CO2 laser resurfacing done under IV sedation or general anesthesia?

Treatment is under local anesthesia with intravenous twilight sedation, given by an anesthesia provider and monitored throughout, in our AAAHC-accredited surgical suite in Syracuse; general anesthesia is not used. Sedation is not a safety feature, since it adds anesthetic risk, and the accredited setting is what makes it appropriate.

How long is recovery after CO2 laser resurfacing?

It depends on the settings. In a 2024 trial one high-setting session averaged 7.3 days of downtime and a staged group 4.3 days in total. The skin closes by about day 7 to 10 in published series, and consensus reports 8 to 42 days. Our sheet says redness fades over about four weeks and sometimes takes months.

What should I avoid after CO2 laser, and when can I wear makeup?

Our sheet asks for no soap on the lasered skin, no picking at crust, and no makeup or cream on the treated area unless our office prescribes it. Once initial healing has taken place, residual redness can be covered with makeup. A retinoid used before treatment resumes at four to six weeks.

When can I go in the sun after CO2 laser?

Our rule is four weeks of complete sun avoidance with a brimmed hat outdoors, then SPF 30 whenever in the sun, with the hat continuing. Sun during healing is the single modifiable driver of hyperpigmentation. Published guidance commonly asks for longer: every panelist in the 2025 consensus advises several months.

Are CO2 laser results permanent, and how long do they last?

The collagen made is the patient's own, and the result develops over three to six months. It is not permanent, and we will not use that word: photoaging continues because sun and time continue, so a resurfaced face keeps aging from a better starting point.

How many sessions will I need, and how much time between treatments?

The conservative route is two to four sessions at six to eight week intervals; the published mean was 2.4 sessions. The single-session route is one deeper treatment, with three to six months before re-treatment. Skin type mostly decides: one high-setting treatment in types I and II, several mild-to-moderate treatments in types III and IV.

Is one deep treatment better than several lighter ones?

Not on the evidence. In a 2024 trial of 44 patients the staged group scored better on most scales, had no adverse events and less total downtime, 4.3 days against 7.3, and both groups reached the same band of global improvement. One deeper session buys fewer episodes: one anesthetic, one recovery. That is a legitimate trade, and it is not a better result.

How much does CO2 laser resurfacing cost, and does insurance cover it?

We do not publish figures, because a number quoted before the skin is examined is a guess; depth, area and anesthesia setting vary by a factor of several. The fee has three parts, the surgeon, the accredited suite and the anesthesia provider; the full figure is given in writing first. Health insurance does not cover cosmetic resurfacing.

Is CO2 laser resurfacing dangerous?

It carries real, quantified risks, which is not the same as dangerous. Hyperpigmentation is the most common, met by 95 percent of the expert panel; infection ran 4.3 percent, herpes reactivation 7.4 percent in a 500-patient series, and hypertrophic scarring 0.46 percent. The most important long-term risk is delayed hypopigmentation. Sedation adds its own risks.

Can CO2 laser cause permanent light patches?

It can, and one should assume it is permanent. Hypopigmentation after ablative resurfacing may not appear for six to 12 months or longer, which is why short follow-up understates it, and it is not reliably treatable. Fractional delivery at moderate settings has largely reduced it, though 47 percent of the expert panel have still encountered it.

Is CO2 laser safe for Fitzpatrick type IV to VI skin, and will it cause dark spots?

Hyperpigmentation depends strongly on skin type: 68 percent in type IV after fully ablative treatment, and 55.5 percent at one month after a single fractional session, falling to 11.1 percent by six months. We treat type IV conservatively and in stages, and generally direct types V and VI to alternatives.

Does CO2 laser treatment cause cancer?

There is no evidence that it does, and the mechanism argues against it: the beam is infrared light at 10,600 nanometers, non-ionizing and absorbed by water, without the photon energy that makes ultraviolet light mutagenic. In a randomized trial, laser-assisted photodynamic therapy cleared 88 percent of grade II to III actinic keratoses against 59 percent without the laser.

Can I have CO2 laser resurfacing at the same time as a facelift or eyelid surgery?

Often yes, though not everywhere at the same settings. Across 17 studies and 1,361 patients, skin slough was 0.21 percent, but lasering undermined skin at the same energy density as non-dissected skin was associated with more of it. The central face is treated at full depth, and the undermined lateral flap is left alone or treated superficially.

The evidence behind this page

Levy T, et al. Expert consensus, fractional ablative CO2 for facial rejuvenation. Lasers Surg Med, 2025.

Tierney EP, Hanke CW. Fractionated CO2 laser for photoaging, 45 patients. Dermatol Surg, 2011.

Caprari E, et al. Lidocaine/tetracaine peel cream for fractional laser pain. J Cosmet Dermatol, 2022.

Shenhav LT, et al. Single high-setting versus multiple low-to-moderate treatments. Lasers Surg Med, 2024.

Nanni CA, Alster TS. Complications of CO2 laser resurfacing, 500 patients. Dermatol Surg, 1998.

Salles AG, et al. Fractional CO2 in phototypes III to VI, burn sequelae. Plast Reconstr Surg, 2018.

Chapas AM, et al. CO2 ablative fractional resurfacing of acneiform scarring. Lasers Surg Med, 2008.

Togsverd-Bo K, et al. Fractional CO2 with photodynamic therapy for actinic keratoses. Br J Dermatol, 2012.

Mirza HN, et al. Ablative versus nonablative resurfacing, 1,093 patients. Dermatol Ther, 2021.

Wen YE, et al. Laser resurfacing at the time of facelift: meta-analysis. Aesthet Surg J, 2026.

Kim JS, et al. Ablative CO2 resurfacing of the lower eyelids. Ophthalmic Plast Reconstr Surg, 2021.

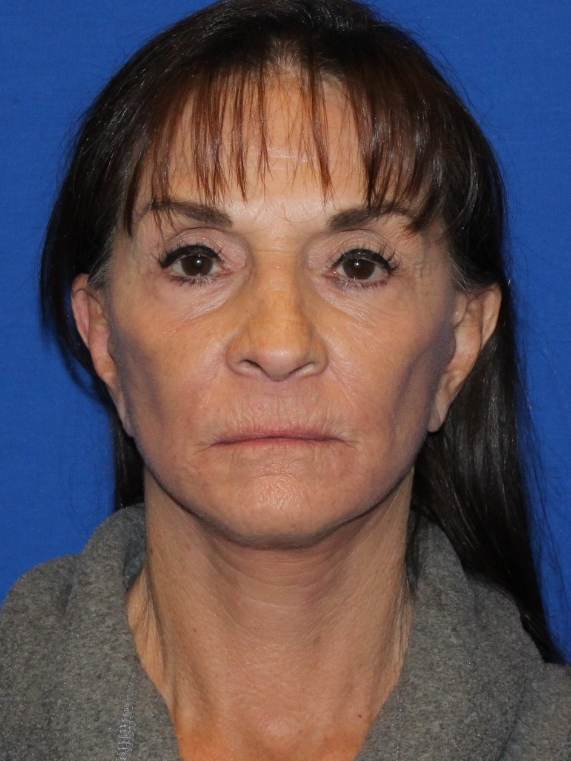
Actual patients of Dr. Kim

Shown with patient consent. Individual results vary by anatomy, technique, and healing.

Laser Skin Resurfacing patient before, front view Laser Skin Resurfacing patient after, front view
Case 1Before (left) & after (right) — front view

View More Laser Skin Resurfacing Results in the Full Gallery →

This page is provided for education and is not medical advice. Reading it does not create a physician–patient relationship. No result shown or described is a guarantee; individual results vary by anatomy, skin type, technique and healing, and every treatment decision should be made in consultation with a qualified physician who has examined you.

Where Surgery Takes Place

Consultations are available at our Rochester and Manhattan offices. This procedure is performed in Syracuse, New York, at our accredited surgical suite, and patients travel to Syracuse for the procedure.

Patients from New York City return home after the procedure and are seen for the one-week visit at our Manhattan office. Patients from Rochester stay at a local hotel the first night and then return home.

Our Offices

Syracuse

4939 Brittonfield Pkwy, Bldg B, Ste 208, East Syracuse, NY 13057. Main office and location of the accredited surgical suite. 315-471-8404. Syracuse Office →

Rochester

70 East Boulevard, Rochester, NY 14610. Consultation and follow-up office, with a travel program for surgical patients. Rochester Office →

Manhattan / Sutton Place

347 E 53rd St, Suite Lobby A, New York, NY 10022. Consultation and follow-up office for NYC patients. 929-291-0922. Manhattan Office →

Schedule a Consultation →

In their own words

"Dr. Kim and his staff are amazing. Very knowledgeable and professional. I always feel comfortable and well taken care of."

L.R. — Google

"Wonderful experience from start to finish. Highly recommend Dr. Kim and his team."

S.T. — Google

"Professional, caring, and the results speak for themselves."

K.W. — Google
Featured In
AllureMarie ClaireChicago TribuneDaily MailGood HousekeepingWCNY (PBS)NewsChannel 9 WSYR (ABC)